
Rotator Cuff Tears
Do all rotator cuff tears need surgery? No. Most do not. A rotator cuff tear is one of the most common findings in an adult shoulder, and many people have one without knowing it. A full-thickness tear will not heal back to the bone on its own, so the question is not whether the tendon is torn but whether this is a tear that will stay quiet or one that should be repaired. That depends on how it happened, how it is behaving, and what you need the shoulder to do.
Dr. Brett Raynor is a fellowship-trained orthopaedic sports medicine surgeon in Dallas who evaluates and treats rotator cuff tears every clinic day. His approach is the same for every patient: understand the tear, start with the simplest treatment that works, and operate when the shoulder has shown it needs it. If an injury has left your shoulder weak, or you already have an MRI showing a tear, the Fast Track page explains how to be seen quickly.
Key points
Tears come in two kinds: degenerative tears that develop over years, and traumatic tears from an injury. They are treated differently.
More than half of adults over 60 have a tear and no symptoms. A tear on a scan is a finding, not an automatic operation.
About three out of four degenerative full-thickness tears are managed successfully without surgery.
Traumatic tears with weakness are repaired early, ideally within a few months of the injury.
What is the rotator cuff, and what does a tear mean?
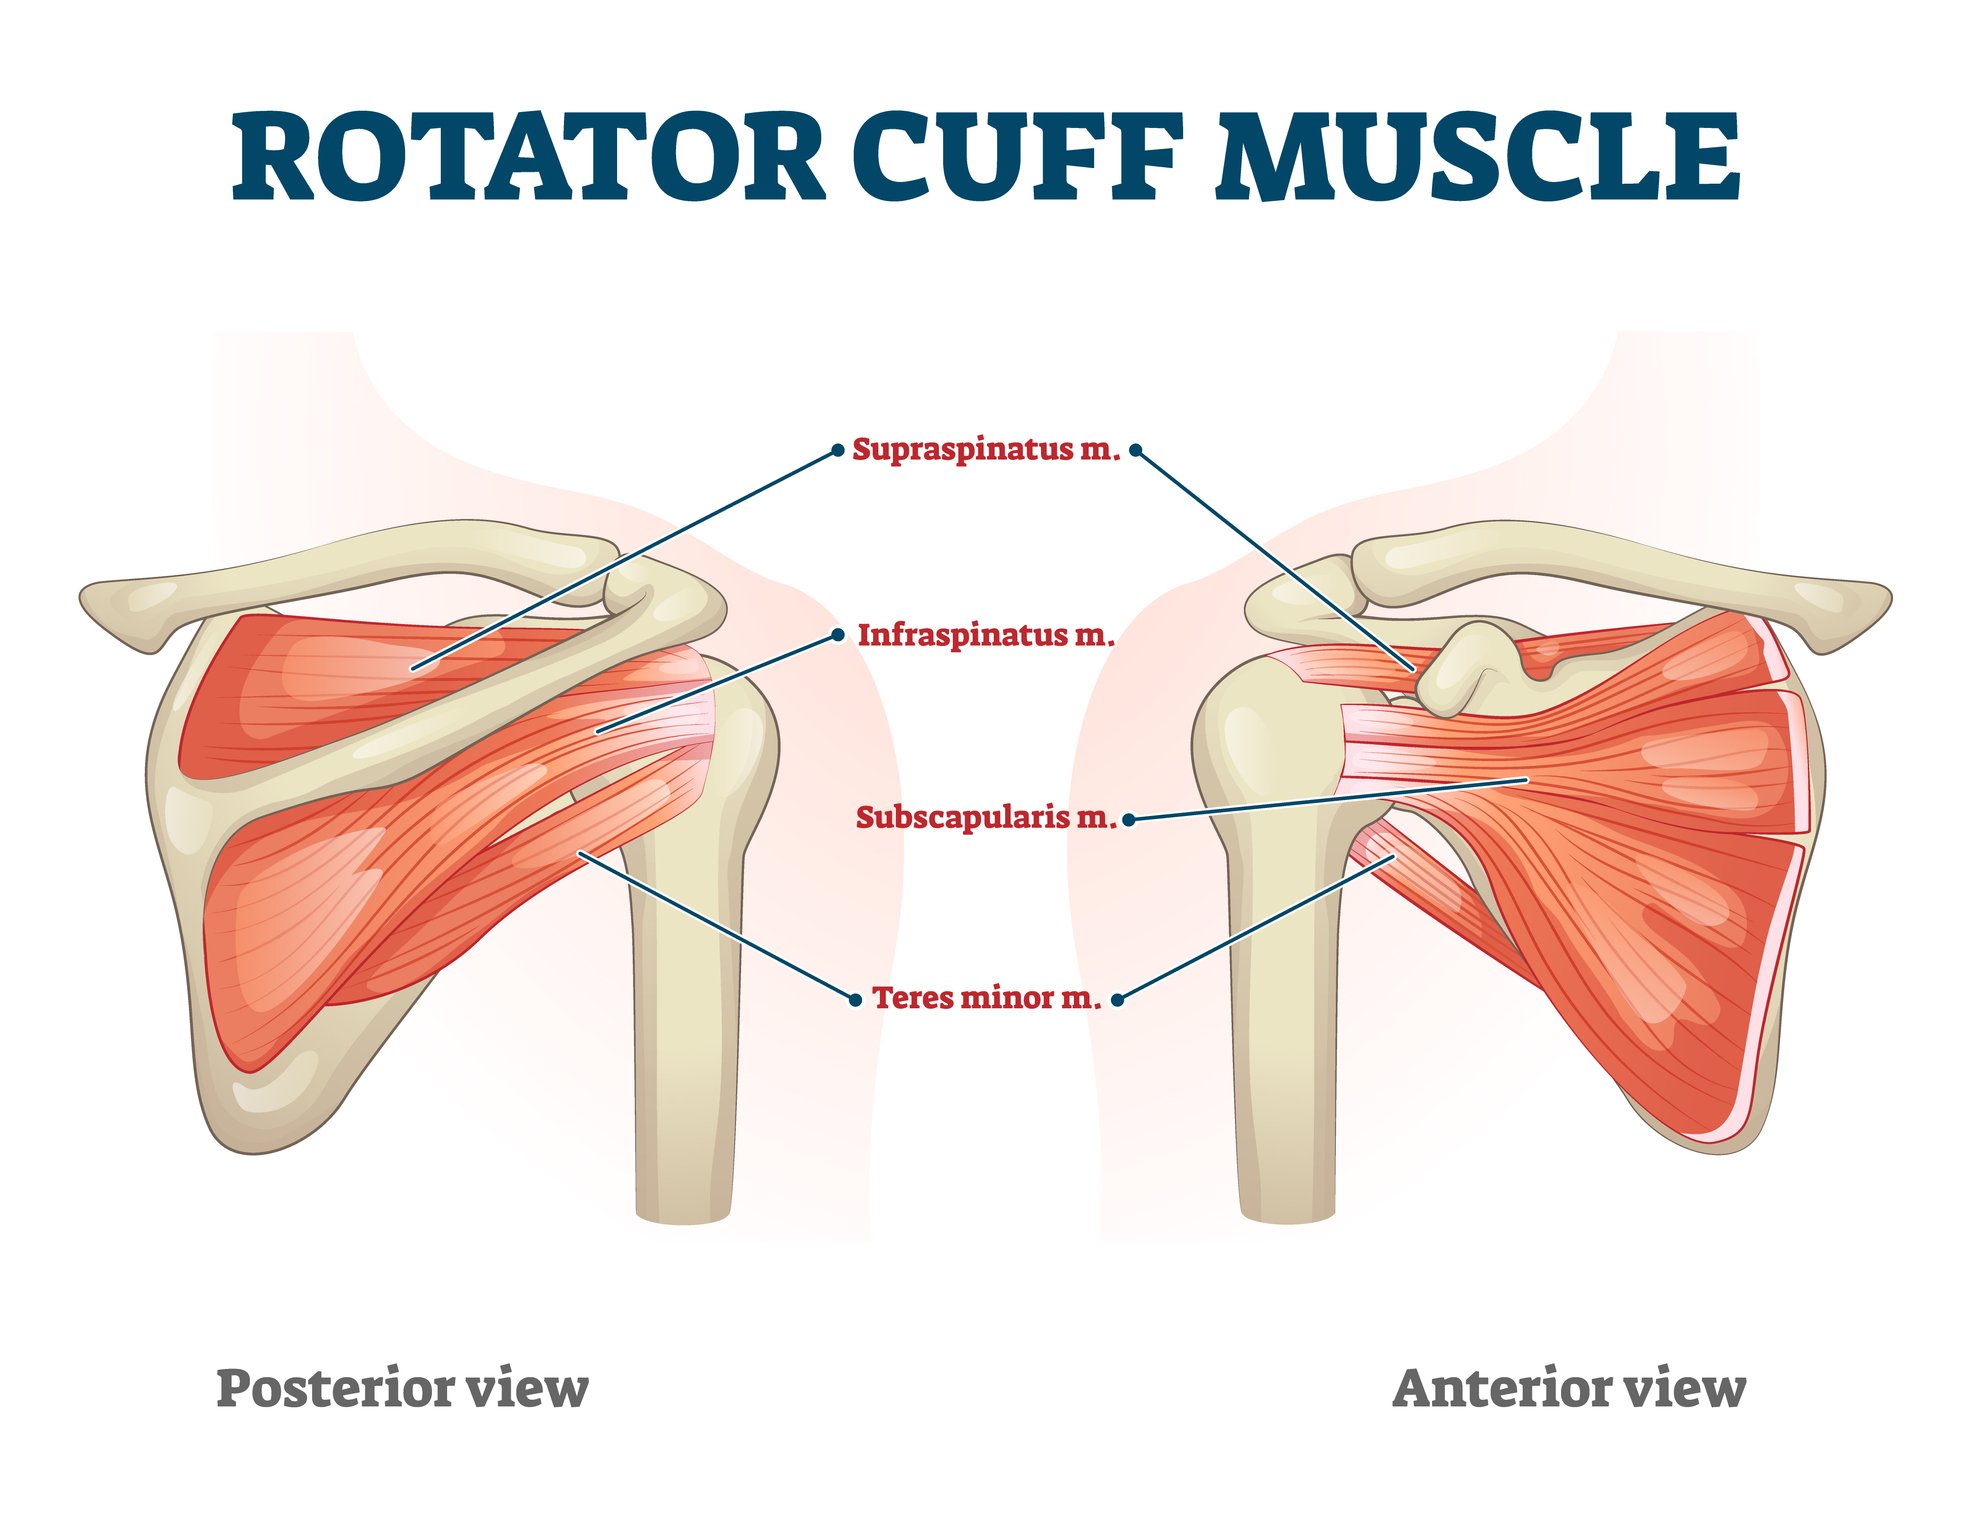
The shoulder is a ball-and-socket joint. The rotator cuff is a group of four tendons deep inside the shoulder that connect the muscles of the shoulder blade to the ball and help start every movement of the arm: one on top, one in front, and two around the back. A rotator cuff tear means one of those tendons has pulled partly or completely away from the bone where it attaches. The top tendon, the supraspinatus, is the one that tears most often.
The biceps tendon runs through a tight groove at the front of the shoulder, immediately next to the cuff. It is a frequent source of pain in the front of the shoulder, either from irritation or because a nearby tear has unsettled it, which is why Dr. Raynor often addresses it at the same time as the cuff.
Two kinds of rotator cuff tears
Degenerative tears develop gradually over years as the tendon frays where it passes under the bone above it. This is the common kind in patients over fifty. Many cause no symptoms until something irritates the shoulder, and when they do hurt there is time to settle them without surgery. Repair is the next step if the shoulder cannot be settled, not the first.
Traumatic tears happen to a shoulder that was working normally until a fall or a sudden pull tore the tendon from the bone. The arm is weak right away, and patients often cannot lift it above shoulder level. These tears are usually larger, the muscle has not had years to adapt, and they are repaired early. In a prospective study of painful traumatic tears with weakness, outcomes were not compromised when repair was done within four months of the injury, and the largest tears repaired after four months had the worst results (Petersen and Murphy, J Shoulder Elbow Surg, 2011).
A partial-thickness tear goes part of the way through the tendon. A full-thickness tear goes all the way through, which can mean anything from a small opening to a tendon that has pulled well away from the bone. Tear size, how far the tendon has retracted, and the condition of the muscle behind it matter more than the label.
Click through the interactive guide below to see how Dr. Raynor explains shoulder pain and its causes in clinic.
The walkthrough as text
The same walkthrough you can tap through above, written out so you can read it, print it or search it. Dr. Raynor narrates it in his own words. Tap a chapter to open it.
This short guide covers how the shoulder works, why it hurts, and what we can do about it, using the same illustrations I use in the exam room. It takes about three minutes.
1. How your shoulder works
- The shoulder is a ball-and-socket joint. The ball is the top of the arm bone (humerus), and the socket is part of the shoulder blade.
- The rotator cuff is a group of four tendons that surround the ball. One runs across the top, one across the front, and two across the back. Together they keep the ball centered in the socket and help you lift and rotate your arm.
- The biceps tendon runs up the front of the arm, turns sharply through a narrow groove, and attaches at the top of the socket. That turn is a common source of pain.
- Between the rotator cuff and the bone above it is a small fluid-filled sac called a bursa. It allows the tendons to glide smoothly.
2. Why it hurts
- Raising the arm overhead brings the top of the humerus up beneath the acromion, the bony roof of the shoulder. The bursa and the rotator cuff tendon are compressed between them, and with repetition both can become inflamed: bursitis and tendinitis.
- When the bursa becomes irritated, it swells and becomes painful. This is called bursitis, and it is one of the most common causes of shoulder pain.
- A tendon can be painful without being torn. Irritation of the tendon from repeated use is called tendinitis, and it usually occurs together with bursitis.
- Sometimes a tendon tears all the way through and pulls away from the bone. Whether the opening is small or large, this is called a full-thickness tear.
- Rotator cuff tears are common, and many cause no pain. In people over 60 without shoulder pain, more than 1 in 4 have a full-thickness rotator cuff tear on MRI, and about half have some tearing. A tear on an MRI does not, by itself, mean surgery.
- Not all rotator cuff tears are alike. Tears that develop gradually over time often do well without surgery. A tear caused by a fall or other injury is different: if the arm suddenly becomes weak or hard to lift, that kind of tear usually does best when it is repaired sooner rather than later. Let me know if an injury started your symptoms.
3. Treatment options
- Most shoulder pain improves without surgery. We begin with the simplest treatments and move up only if needed. Physical therapy is always a reasonable choice.
- For a full-thickness tear that developed without an injury, physical therapy is usually the first step. Most people who complete a course of therapy do not need surgery, and trying therapy first does not rule surgery out.
4. If surgery is needed
- If surgery is needed, the tendon is reattached to the bone with small anchors so it can heal back in place. The procedure is done arthroscopically, through a few small incisions.
- If the biceps tendon is contributing to the pain, it can be moved slightly lower on the arm so it no longer passes through the narrow groove. This adds only a few minutes to the surgery.
- Tendon-to-bone healing takes time. You will wear a sling for six weeks and begin strengthening at about three months. The tendon is healed at about four months, most people return to their usual activities by six months, and full recovery takes about a year.
Before your visit
If you are scheduled to see me, here are a few things to consider before your visit, so we can make the most of our time together:
Things to consider
- Where exactly does it hurt? Be ready to point to it.
- Did it start with a fall or an injury, or come on gradually?
- Does it wake you up at night?
- What makes it worse: reaching overhead, behind your back, lifting?
- What have you already tried: therapy, medicine, a shot?
- What do you want to get back to doing?
Questions you may want to ask
- Is it torn, or is it irritated?
- What happens if I wait?
- What can I do at home in the meantime?
- What’s the next step for me?
Symptoms of a rotator cuff tear
Pain on the outside of the upper arm, typically worse at night and when lying on that side
Pain or weakness when lifting the arm, reaching overhead, or reaching behind you
Pain in the front of the shoulder, where the biceps tendon runs
Pain that travels down toward the middle of the upper arm
A catching or clicking sensation with certain movements
Sudden weakness after an injury, which is the sign of a traumatic tear
The shoulder can also hurt without being torn. The tendon and the bursa, the thin sac that lets the tendon glide under the bone, can become inflamed from overuse. That is bursitis and tendinitis, and it can be stubborn: once the tendon is irritated, ordinary daily motion keeps re-irritating it, so a shoulder can stay sore for months with nothing structurally wrong.
How common are rotator cuff tears?
Very common, and most cause no symptoms. In an MRI study of adults with no shoulder pain, 54% of those over 60 had a rotator cuff tear, about half of them full-thickness (Sher et al., J Bone Joint Surg Am, 1995). When an entire community was screened by ultrasound, 22% of adults had a full-thickness tear, rising from about 11% in their fifties to 15% in their sixties, 27% in their seventies and 37% in their eighties, and two-thirds of the tears in people over 60 caused no symptoms (Minagawa et al., J Orthop, 2013).
Dr. Raynor's way of putting it: if you scanned the next hundred people over sixty with no shoulder pain, more than half would have a tear. A tear on a scan is a finding, not a reason for an operation by itself.
How is a rotator cuff tear diagnosed?
The examination comes first. A few minutes of strength and motion testing tells Dr. Raynor which tendon is involved, whether the arm is weak or only painful, and whether the biceps is contributing.
X-rays are usually normal. They rule out arthritis, fractures and anything unexpected. A rotator cuff tear is a soft-tissue problem, so a normal X-ray does not mean nothing is wrong.
MRI is ordered when it would change the plan. If the first step is physical therapy or an injection either way, the scan can wait. Dr. Raynor orders an MRI when there was an injury with weakness, when the shoulder has not responded to treatment, or when surgery is being considered and he needs to see exactly what he will be repairing.
Dr. Raynor explains what a rotator cuff MRI shows: partial and full-thickness tears, a tendon that has pulled back, and the muscle behind it. Watch it with chapters and the full transcript.
What happens if a rotator cuff tear is left alone?
Some tears stay quiet for years. Others grow, and a tear that has retracted and lost its muscle may no longer be repairable. The tears that grow are the ones most likely to start hurting, so your shoulder is a pretty good alarm: if pain comes back or the arm starts to feel weak, that is the time to take another look. A known full-thickness tear is not an emergency, but it is worth watching: periodic reassessment keeps your options open even if you never choose surgery. The research behind this is summarized in the expandable sections below.
Treatment without surgery
Dr. Raynor lays out the same options with every patient, starting with the one that gives you the most control.
Observation. A degenerative tear that is not limiting you can be left alone and watched.
Physical therapy. Strengthening the muscles around the cuff takes load off the tendon and often settles the shoulder completely. It is the first step for nearly every degenerative tear, and about three out of four full-thickness degenerative tears are managed this way without surgery.
Anti-inflammatory medication for a flare, if you are able to take it.
A steroid injection to calm the shoulder so therapy can do its work. Dr. Raynor considers an injection that gives three months of relief a good result. One or two are reasonable; a standing schedule of injections in place of a plan is not.
When is surgery the right call?
Dr. Raynor recommends rotator cuff repair when:
The tear was caused by an injury and the arm is weak. These are repaired early, while the tendon is still mobile and the muscle is healthy.
A degenerative tear has not settled after a real trial of therapy and, usually, an injection, and the pain or weakness is limiting your life.
The shoulder is getting weaker, or imaging shows a tear that is growing or retracting.
You are young or active and the tear is likely to progress over the decades you need the shoulder.
The operation is arthroscopic and outpatient, and the tendon is reattached to the bone so it can heal back in. How Dr. Raynor performs rotator cuff repair explains the surgery step by step, and the recovery roadmap walks through the six months that follow. You can also watch his animation of the repair, narrated step by step.
Why patients choose Dr. Raynor for rotator cuff tears
Fellowship-trained in sports medicine at the Steadman Philippon Research Institute in Vail, Colorado
Board-certified orthopaedic surgeon; D Magazine Best Doctor every year since 2019
Team physician for the U.S. Ski and Snowboard Team, Highland Park High School, St. Mark's School of Texas, Hockaday and Ursuline Academy
Published shoulder research presented at the American Orthopaedic Society for Sports Medicine
More than 800 five-star Google reviews
The research, and common questions
Expand any section below. Further down, Dr. Raynor answers questions about rotator cuff surgery on video.
-
In a Washington University study that followed people with a tear that was not causing pain, the tear enlarged in 49% of shoulders over about five years, in 61% of full-thickness tears, and about half of the patients developed new pain. Shoulders whose tear enlarged were far more likely to show wasting of the muscle behind it (Keener et al., J Bone Joint Surg Am, 2015). In the same group's patients aged 65 and younger, followed for a median of seven years, 60% of tears enlarged, and only 42% of full-thickness tears were still the same size at five years (Torchia et al., J Shoulder Elbow Surg, 2023). The tears that grow are the ones most likely to start hurting: in the same group's research, shoulders that started to hurt were more likely to have a tear that had grown (Keener et al., J Bone Joint Surg Am, 2015; Mall et al., J Bone Joint Surg Am, 2010). So your shoulder is a pretty good alarm. If pain comes back or the arm starts to feel weak, have the tear rechecked before it gets harder to fix.
-
In a multicenter study of 452 patients with full-thickness tears that were not caused by an injury, about 75% were treated successfully with physical therapy and did not need surgery over two years of follow-up. The patients who did choose surgery usually decided within the first 6 to 12 weeks, and few chose it after that (Kuhn et al., J Shoulder Elbow Surg, 2013). In the same group, the strongest predictor of ending up in surgery was not the size of the tear but how little the patient expected therapy to help (Dunn et al., J Shoulder Elbow Surg, 2016). Doing the work matters.
-
Repeated injections can weaken the tendon. In a systematic review, patients who had two or more steroid injections in the year before a rotator cuff repair were about two to three times as likely to need revision surgery (Cimino et al., Arthroscopy, 2020). That is why Dr. Raynor uses injections deliberately and schedules surgery with some distance from the last one.
-
A full-thickness tear does not reattach to the bone on its own. A partial tear or an irritated tendon can settle completely. Either can become pain-free without surgery; the tear itself does not close.
-
Not right away in most cases. If the first step is therapy or an injection regardless of what the scan shows, the scan can wait. Dr. Raynor orders an MRI when it will change the plan, and always before surgery. If you already have one, this short video shows what Dr. Raynor looks for on a rotator cuff MRI.
-
Often, yes, with adjustments. Activity below shoulder level is usually fine, and physical therapy will guide what to add back. Soreness afterward is information rather than damage. Weakness after an injury is different: stop and have the shoulder examined.
-
Usually, yes. Options include partial repair, reinforcing the repair with a graft, using the biceps tendon to cover the gap, and a balloon spacer. A reverse shoulder replacement can be the better option when the cuff cannot be repaired and the ball has ridden up toward the bone above it; when an older patient's tear cannot be fixed; when the front tendon (the subscapularis) is also torn and the arm cannot be lifted actively, which is called pseudoparalysis; or when the tear has gone on to arthritis. Dr. Raynor performs these reconstructions, and shoulder replacement in carefully selected patients, and will tell you which one fits your shoulder. Dr. Raynor explains each option on the massive and irreparable rotator cuff tears page.
-
A sling for six weeks, physical therapy for several months, strengthening from three months, and most patients doing everything they want to do by four to six months. The recovery roadmap covers every stage, and the rotator cuff repair FAQs answer the day-to-day questions.
-
Sher JS, et al. Abnormal findings on magnetic resonance images of asymptomatic shoulders. J Bone Joint Surg Am. 1995;77(1):10-15. doi:10.2106/00004623-199501000-00002
Minagawa H, et al. Prevalence of symptomatic and asymptomatic rotator cuff tears in the general population: from mass-screening in one village. J Orthop. 2013;10(1):8-12. doi:10.1016/j.jor.2013.01.008
Keener JD, et al. A prospective evaluation of survivorship of asymptomatic degenerative rotator cuff tears. J Bone Joint Surg Am. 2015;97(2):89-98. doi:10.2106/JBJS.N.00099
Mall NA, et al. Symptomatic progression of asymptomatic rotator cuff tears: a prospective study of clinical and sonographic variables. J Bone Joint Surg Am. 2010;92(16):2623-2633. doi:10.2106/JBJS.I.00506
Torchia MT, et al. Evaluation of survivorship of asymptomatic degenerative rotator cuff tears in patients 65 years and younger. J Shoulder Elbow Surg. 2023;32(7):1432-1444. doi:10.1016/j.jse.2023.03.008
Kuhn JE, et al. Effectiveness of physical therapy in treating atraumatic full-thickness rotator cuff tears: a multicenter prospective cohort study. J Shoulder Elbow Surg. 2013;22(10):1371-1379. doi:10.1016/j.jse.2013.01.026
Dunn WR, et al. 2013 Neer Award: predictors of failure of nonoperative treatment of chronic, symptomatic, full-thickness rotator cuff tears. J Shoulder Elbow Surg. 2016;25(8):1303-1311. doi:10.1016/j.jse.2016.04.030
Petersen SA, Murphy TP. The timing of rotator cuff repair for the restoration of function. J Shoulder Elbow Surg. 2011;20(1):62-68. doi:10.1016/j.jse.2010.04.045
Cimino AM, et al. Corticosteroid injections may increase retear and revision rates of rotator cuff repair: a systematic review. Arthroscopy. 2020;36(8):2334-2341. doi:10.1016/j.arthro.2020.04.044
What is a rotator cuff tear, and how does surgery fix it?
How is rotator cuff surgery performed?
What is recovery like after rotator cuff surgery?
How can I prepare for rotator cuff surgery?
If another doctor has already told you that you need surgery, see getting a second opinion on a rotator cuff tear. You can also read why patients choose Dr. Raynor as their Dallas rotator cuff surgeon.
Make an appointment
Call (214) 265-3211, schedule online, or send an appointment request. Texas Orthopaedic Associates, 7115 Greenville Avenue, Suite 310, Dallas, TX 75231.
Written and medically reviewed by M. Brett Raynor, M.D., board-certified orthopaedic sports medicine surgeon. Last reviewed 10/10/2026. General information for patients; it does not replace an examination.